Back Dermal Piercing Pain Level Assessment And Management
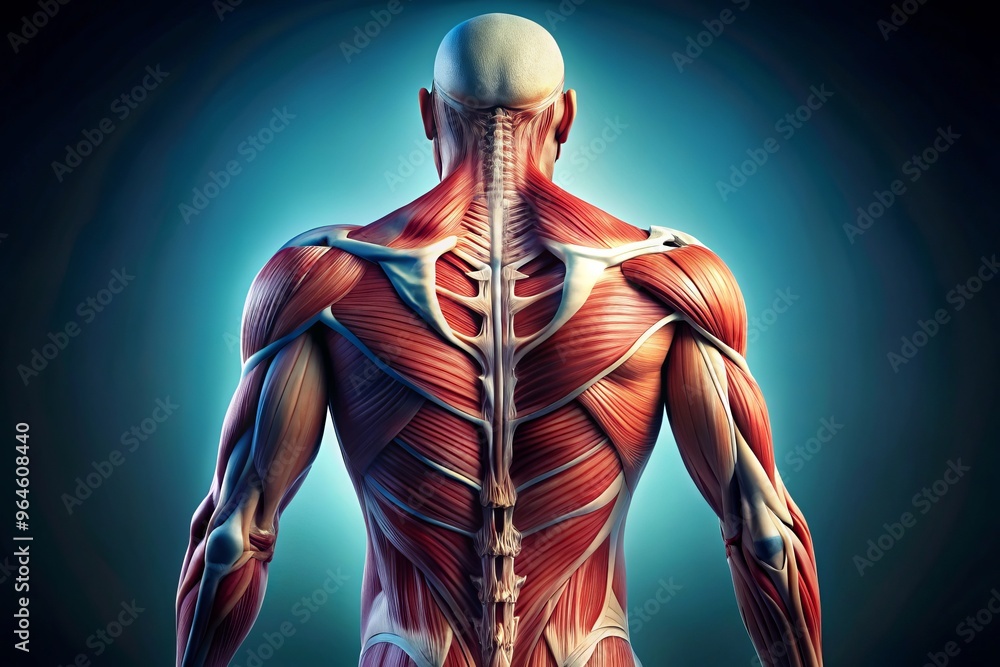
Table of Contents
- Anatomy and Placement Considerations for Back Dermal Piercings
- Dermis Thickness and Sensitivity Variations Across Back Zones
- Surface vs. Deep Dermal Placements: Impact on Pain and Healing
- Nerve Pathways Influencing Pain in Back Dermal Piercings
- Pain Mechanisms and Procedural Dynamics in Back Dermal Piercing
- Physiological Pain Triggers in Back Dermal Piercing
- Step-by-Step Procedural Pain Intensity Profile
- Factors Influencing Pain Levels in Back Dermal Piercing
- Comparative Pain Profiles: Back Dermal vs. High-Sensitivity Piercings
- Pain Management Techniques in Back Dermal Piercing
- Pre-Piercing Pain Mitigation Methods
- Post-Piercing Pain Relief Protocol
- Advanced Pain Management for High-Tolerance Clients
- Healing Process and Pain Evolution Over Time in Back Dermal Piercings
- Pain Progression During Healing Stages
- Common Healing Complications and Pain Exacerbation
- Regional Variations in Healing Pain and Duration
Back dermal piercings present a unique intersection of aesthetic expression and physiological challenge, where anatomical complexity directly influences pain perception and healing outcomes. Unlike superficial piercings, the back’s layered musculature, variable dermis depth, and dense nerve networks create distinct pain thresholds across regions, demanding precise placement and tailored pain management strategies. Understanding these factors is essential for both practitioners and clients to navigate the procedure with informed expectations and optimized comfort.
The experience of pain during and after a back dermal piercing is not uniform; it varies significantly based on needle depth, jewelry type, and individual tissue sensitivity. Surface placements may induce a sharp, transient sensation, while deeper anchors engage muscle fibers and nerves, prolonging discomfort. This analysis explores the anatomical underpinnings of pain, procedural variables, and evidence-based mitigation techniques to ensure a safer, more tolerable journey from piercing to full healing.
Anatomy and Placement Considerations for Back Dermal Piercings
The placement of back dermal piercings involves navigating a complex interplay of muscular, neural, and vascular structures, where anatomical variations significantly influence pain perception, healing trajectories, and potential complications. The dermis of the back exhibits distinct thickness and sensitivity gradients across three primary zones—upper (thoracic), middle (lumbar), and lower (sacral)—each requiring tailored assessment for optimal piercing outcomes. Understanding these anatomical nuances ensures safer execution, minimizes trauma, and aligns expectations for post-procedure discomfort and recovery.The back’s superficial and deep layers house critical structures that dictate piercing feasibility. The thoracic region (upper back) is dominated by the trapezius and rhomboid muscles, underlain by intercostal nerves and vascular plexuses, while the lumbar region (middle back) features broader dermis with fewer nerve clusters but greater muscle mass (e.g., latissimus dorsi). The sacral region (lower back) presents thinner dermis with heightened sensitivity due to proximity to the spinal nerves (dorsal rami) and sacral plexus. These variations necessitate precise depth control to avoid penetrating deeper tissues, which could compromise vascular integrity or irritate neural pathways.
Dermis Thickness and Sensitivity Variations Across Back Zones
The dermis of the back demonstrates measurable depth and sensitivity disparities, directly impacting pain tolerance and healing dynamics. Below is a structured comparison of key regions, incorporating dermis thickness (measured via ultrasound or cadaveric studies), subjective pain sensitivity (scaled 1–10 based on clinical observations), and common piercing sites. Sensitivity levels reflect average patient responses during piercing, with adjustments for individual variability (e.g., nerve density, scar tissue, or pain thresholds).| Region | Dermis Depth (mm) | Pain Sensitivity Level (1–10) | Common Piercing Sites |
|---|---|---|---|
| Upper Back (Thoracic) | 1.2–2.0 mm (superficial); 3.0–5.0 mm (deep) | 6–8 (high due to intercostal nerves and muscle tension) | Between scapulae, suprascapular ridge, mid-thoracic spine |
| Middle Back (Lumbar) | 1.5–2.5 mm (superficial); 4.0–6.0 mm (deep) | 4–6 (moderate; broader dermis dilutes nerve density) | Lumbar triangle (Petit’s triangle), paraspinal lines |
| Lower Back (Sacral) | 0.8–1.5 mm (superficial); 2.0–3.5 mm (deep) | 7–9 (extreme due to dorsal rami and sacral plexus proximity) | Sacral hiatus, iliac crests, coccygeal region |
Surface vs. Deep Dermal Placements: Impact on Pain and Healing
The depth of a back dermal piercing directly correlates with pain intensity during insertion, immediate post-procedure discomfort, and long-term healing stability. Surface placements (≤1.5 mm depth) target the papillary dermis, where nerve endings are concentrated but vascular disruption is minimal. Deep placements (≥2.5 mm) extend into the reticular dermis, engaging larger nerve bundles (e.g., dorsal rami) and increasing the likelihood of muscle or ligament irritation.Comparative Analysis:
Optimal Depth Guidelines:
For back dermal piercings, a 1.8–2.2 mm insertion depth (measured from skin surface to jewelry base) balances pain management and retention. This range avoids superficial migration while minimizing deep-tissue trauma. Piercers should use digital calipers or ultrasound guidance to verify depth, especially in high-sensitivity zones (e.g., sacral region).
Nerve Pathways Influencing Pain in Back Dermal Piercings
The back’s neural architecture comprises somatic sensory nerves that transmit pain signals during and after piercing. Key pathways include the intercostal nerves (ventral rami of thoracic spinal nerves), dorsal rami (posterior branches supplying paraspinal muscles), and cluneal nerves (innervating the sacral area). Disruption of these nerves—either directly by the piercing needle or indirectly via tissue swelling—contributes to acute and chronic pain.Visual Description of Critical Nerve Pathways:
Mitigation Strategies:
- Intercostal Nerves (T2–T12):
Originate from thoracic spinal nerves, running between ribs in the costal grooves. Piercings in the upper back (e.g., suprascapular ridge) may stimulate these nerves, causing radiating pain along dermatomal lines (e.g., T4–T6 for shoulder blades).
- Avoidance Zones: 2 cm lateral to the thoracic spine; 3 cm below the scapular spine.
- Pain Pattern: Sharp, electric-like sensations during insertion; referred pain to anterior chest/abdomen post-procedure.
- Dorsal Rami (Posterior Branches of Spinal Nerves):
Divide into medial branches (supplying multifidus muscles) and lateral branches (innervating skin/muscles of the back). The greater occipital nerve (C2) and dorsal rami of L1–S3 are particularly sensitive.
- Avoidance Zones: Directly over spinous processes; sacral hiatus (L5–S2 dorsal rami).
- Pain Pattern: Deep, aching discomfort; potential hyperalgesia (increased sensitivity) lasting weeks.
- Cluneal Nerves (Superior, Middle, Inferior):
Innervate the sacral and gluteal regions. The superior cluneal nerves (L1–L3) emerge near the iliac crests, while the middle cluneal nerve (S1–S3) supplies the lower sacrum.
- Avoidance Zones: 5 cm lateral to the sacral spine; coccygeal region.
- Pain Pattern: Burning or "pins-and-needles" sensation; risk of neuropathic pain if nerves are compressed.
Pain Mechanisms and Procedural Dynamics in Back Dermal Piercing
The perception of pain during back dermal piercing procedures is influenced by a complex interplay of physiological trauma, anatomical variability, and mechanical stimuli. Unlike superficial piercings, back dermals engage deeper tissue layers, including muscle fascia, subcutaneous fat, and neurovascular bundles, which heighten sensory responses. Understanding these mechanisms—such as ischemia from tissue displacement, nerve compression, and differential pain thresholds across muscle groups—allows practitioners to anticipate discomfort and tailor techniques to minimize distress. This section examines the step-by-step pain triggers, procedural variables affecting intensity, and comparative sensory profiles relative to other high-sensitivity piercings.Physiological Pain Triggers in Back Dermal Piercing
Back dermal piercings activate multiple pain pathways due to the region’s dense muscular and adipose distribution. The primary triggers include:Key anatomical considerations:
The upper back (e.g., scapular region) features thinner fat layers and closer proximity to nerves (e.g., intercostal branches), while the lower back (e.g., lumbar area) has thicker adipose tissue but higher muscle density, altering pain distribution. Blockquote: "Pain perception in dermals correlates with needle trajectory: vertical insertions risk deeper nerve penetration, whereas horizontal placements may compress superficial sensory fibers."
Step-by-Step Procedural Pain Intensity Profile
The following stages outline pain progression, categorized by tissue interaction and mechanical stress. Pain levels are subjective but can be generalized using a 0–10 scale (0 = no pain, 10 = excruciating), with variations based on individual thresholds and placement depth.-
Surface marking and antisepsis:
Minimal pain (1–2/10). Involves alcohol swabbing and superficial pressure to outline placement; sensory input is limited to epidermal stimulation. -
Needle entry (epidermis to dermis):
Sharp, brief sting (4–6/10). Disruption of keratinized layers and superficial capillaries triggers immediate mechanoreceptor activation. Pain peaks at ~2–3mm depth due to dense nerve endings in the papillary dermis. -
Dermal layer penetration (target depth):
Dull, pressing ache (5–8/10). As the needle traverses the reticular dermis (1–4mm depth), collagen fibers and neurovascular plexuses are displaced. Deep placements (>5mm) may induce muscle fascia engagement, increasing pain to 7–9/10 due to nerve root compression (e.g., dorsal rami). -
Jewelry insertion:
Transient sharpness (3–7/10) followed by pressure (4–6/10). The initial stretch of the piercing channel can reactivate mechanoreceptors, while jewelry (e.g., internal anchors) may cause localized ischemia if too tight. Barbells distribute pressure more evenly than straight needles, reducing peak discomfort. -
Initial swelling (first 24–48 hours):
Dull, throbbing ache (3–5/10). Edema increases intra-tissue pressure, compressing nerves and blood vessels. Pain often worsens with movement (e.g., sitting, lying down) due to muscle engagement. -
Healing progression (beyond 72 hours):
Pain diminishes to 1–3/10 as inflammation resolves, though residual soreness may persist during jewelry adjustments or if scar tissue forms.
Factors Influencing Pain Levels in Back Dermal Piercing
The following table summarizes how procedural variables correlate with perceived pain, based on clinical observations and client feedback. Needle gauge, depth, and jewelry type are critical modifiers, with trade-offs between precision and trauma.| Factor | Impact on Pain | Example |
|---|---|---|
| Needle gauge | Thinner gauges (14G+) reduce initial trauma but may require multiple passes, increasing cumulative pain. Thicker gauges (10G–12G) cause more immediate pressure but faster tissue separation. | 16G needle: 5/10 pain; 10G needle: 7/10 pain (but single-pass efficiency). |
| Piercing depth | Superficial (<3mm) placements yield lower pain (3–5/10) but higher risk of migration. Deep (>5mm) piercings engage muscle fascia, increasing pain to 7–9/10 but improving retention. | Surface dermal: 4/10; Deep dermal (e.g., near scapula): 8/10. |
| Jewelry type | Internal anchors distribute pressure evenly but may cause initial ischemia if oversized. Barbells concentrate force at entry/exit points, increasing localized pain but reducing overall tissue stress. | Internal anchor (6mm diameter): 6/10; Barbell (1.2mm diameter): 5/10. |
| Needle trajectory | Horizontal insertions compress superficial nerves, increasing pain (6–8/10). Vertical trajectories minimize nerve involvement but risk deeper penetration. | Horizontal (parallel to spine): 7/10; Vertical (perpendicular): 5/10. |
| Client anatomy | Thin-fat individuals experience higher pain (6–9/10) due to closer nerve proximity. Thick-fat clients may feel less initial pain (3–5/10) but risk deeper trauma if depth is misjudged. | Client A (5mm fat layer): 8/10; Client B (20mm fat layer): 4/10. |
Comparative Pain Profiles: Back Dermal vs. High-Sensitivity Piercings
Back dermal piercings exhibit unique sensory characteristics distinct from other high-sensitivity placements, primarily due to tissue density and nerve distribution. The following table contrasts pain modalities, healing dynamics, and recovery timelines.| Piercing Type | Primary Pain Sensation | Peak Pain Phase | Healing Duration | Unique Sensory Notes | |||||||||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Back dermal | Dull ache with intermittent sharp pressure | Jewelry insertion (5–8/10) and swelling (3–5/10) | 4–8 weeks (longer if deep) | Pain radiates along muscle groups; movement exacerbates discomfort. Post-healing, may retain slight sensitivity to touch. | |||||||||||||||||||||||||||||||||||||||
| Nipple (male/female) | Sharp, electric sting with referred pain to chest | Needle exit (7–9/10); healing crusting (4–6/10) | 6–12 weeks
Pain Management Techniques in Back Dermal PiercingEffective pain management in back dermal piercings requires a multi-modal approach tailored to individual pain thresholds, anatomical sensitivity, and procedural complexity. Pain perception varies significantly among clients due to factors such as nerve density, psychological resilience, and prior piercing experiences. Proper pre-, intra-, and post-procedural strategies mitigate discomfort, reduce stress, and minimize complications, ensuring a safer and more tolerable experience for both client and practitioner.Pain management in dermal piercings extends beyond immediate procedural relief; it encompasses long-term healing optimization to prevent chronic discomfort or nerve irritation. Advanced techniques, including pharmacological and non-pharmacological interventions, are critical for clients with high pain tolerance or medical conditions affecting pain perception (e.g., fibromyalgia, neuropathy). Below, structured protocols address pre-piercing mitigation, post-procedural care, and specialized interventions for high-risk cases. Pre-Piercing Pain Mitigation MethodsPre-procedural pain management focuses on reducing anxiety, desensitizing the skin, and minimizing physiological stress responses. Techniques range from topical anesthetics to psychological preparation, with selection dependent on client history and piercing location. Topical numbing agents (e.g., lidocaine-prilocaine creams) are most effective when applied 30–60 minutes pre-piercing, though efficacy varies by skin thickness and vascularity. Pressure techniques, such as firm compression or ice application, can dull nerve sensitivity in areas like the upper back or scapular regions. Psychological strategies, including guided breathing, hypnosis, or distraction (e.g., music, conversation), leverage the gate-control theory of pain to reduce perceived intensity.
Topical anesthetics should never be applied to broken or irritated skin, and clients with known allergies to local anesthetics (e.g., amide esters) must be screened pre-procedure. Post-Piercing Pain Relief ProtocolPost-procedural pain in back dermal piercings typically peaks within 24–48 hours due to tissue trauma and inflammatory response. Management strategies prioritize reducing swelling, preventing infection, and modulating nerve sensitivity. Cold therapy is the first-line intervention, followed by pharmacological support and activity restrictions to avoid irritation. Below is a structured timeline for post-piercing care, adapted from clinical guidelines for dermal piercings and wound healing protocols.
Clients with chronic pain conditions (e.g., fibromyalgia) may require extended NSAID use (up to 7 days) or adjunct therapies like gabapentin (off-label), prescribed by a physician. Advanced Pain Management for High-Tolerance ClientsClients with high pain thresholds—often due to prior piercing experience, adrenaline responses, or conditions like endorphin sensitivity—may require advanced interventions to ensure procedural tolerance and post-operative comfort. These methods carry risks and should be administered by trained professionals (e.g., piercers with medical training or collaboratingHealing Process and Pain Evolution Over Time in Back Dermal PiercingsThe healing trajectory of a back dermal piercing is characterized by distinct phases of tissue response, each accompanied by evolving pain patterns influenced by inflammation, cellular repair, and mechanical stress. Understanding this progression allows piercers and clients to differentiate between normal discomfort and complications requiring intervention. Pain intensity and type vary significantly depending on anatomical location, piercing depth, and individual tissue resilience, necessitating a structured approach to monitoring and management.Pain perception in dermal piercings is not linear; it fluctuates in response to physiological changes such as edema, neovascularization, and collagen deposition. The initial trauma phase triggers an acute inflammatory response, while later stages involve remodeling and scar maturation, where discomfort may persist due to friction or muscle tension. Regional differences further complicate pain assessment, as areas with higher muscle density or constant movement (e.g., lower back) experience prolonged irritation compared to relatively static regions (e.g., upper back). Pain Progression During Healing StagesThe healing process of a back dermal piercing can be divided into three primary phases, each with distinct pain characteristics and duration. These stages align with the body’s wound healing timeline but are modified by the piercing’s subdermal placement and lack of an exit point, which delays full stabilization.Phase 1: Initial Trauma and Acute Inflammation (Days 1–7) Phase 2: Subacute Healing and Crusting (Weeks 1–4) Pain intensity during this period is moderate at worst, rarely exceeding a 4/10 on the pain scale, unless complications arise. Clients may also report hypersensitivity to touch, which gradually diminishes as nerve endings regenerate. Phase 3: Remodeling and Maturation (Weeks 4–12+) In some cases, phantom discomfort—a faint, residual ache—may persist for 3–6 months, particularly in highly sensitive individuals or piercings placed near nerve clusters (e.g., near the scapula or lumbar region). This sensation typically resolves as the nervous system adapts to the permanent alteration. Common Healing Complications and Pain ExacerbationComplications in back dermal piercings often manifest as persistent or worsening pain, deviation from the expected healing timeline, or visible abnormalities. These issues can arise from technical errors, client behavior, or anatomical factors, and early recognition is critical to preventing chronic conditions.Warning Signs of Complications and Mitigation Strategies Regional Variations in Healing Pain and DurationThe anatomical location of a back dermal piercing significantly influences pain perception, healing duration, and susceptibility to complications. Factors such as muscle density, movement patterns, and clothing friction create distinct challenges across regions. The following table compares key characteristics of upper and lower back piercings, along with mitigation strategies tailored to each area.
|

Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Staging Shopify Treasuretrails.